Probiotics with antibiotics: benefit depends on strain, timing, and patient risk
Recent reviews support lower antibiotic-associated diarrhea risk, but results cannot be generalized to every probiotic product.

Probiotics may reduce antibiotic-associated diarrhea on average, yet strain identity, viability, baseline risk, and immune status determine relevance.
Probiotic is a category, not an ingredient
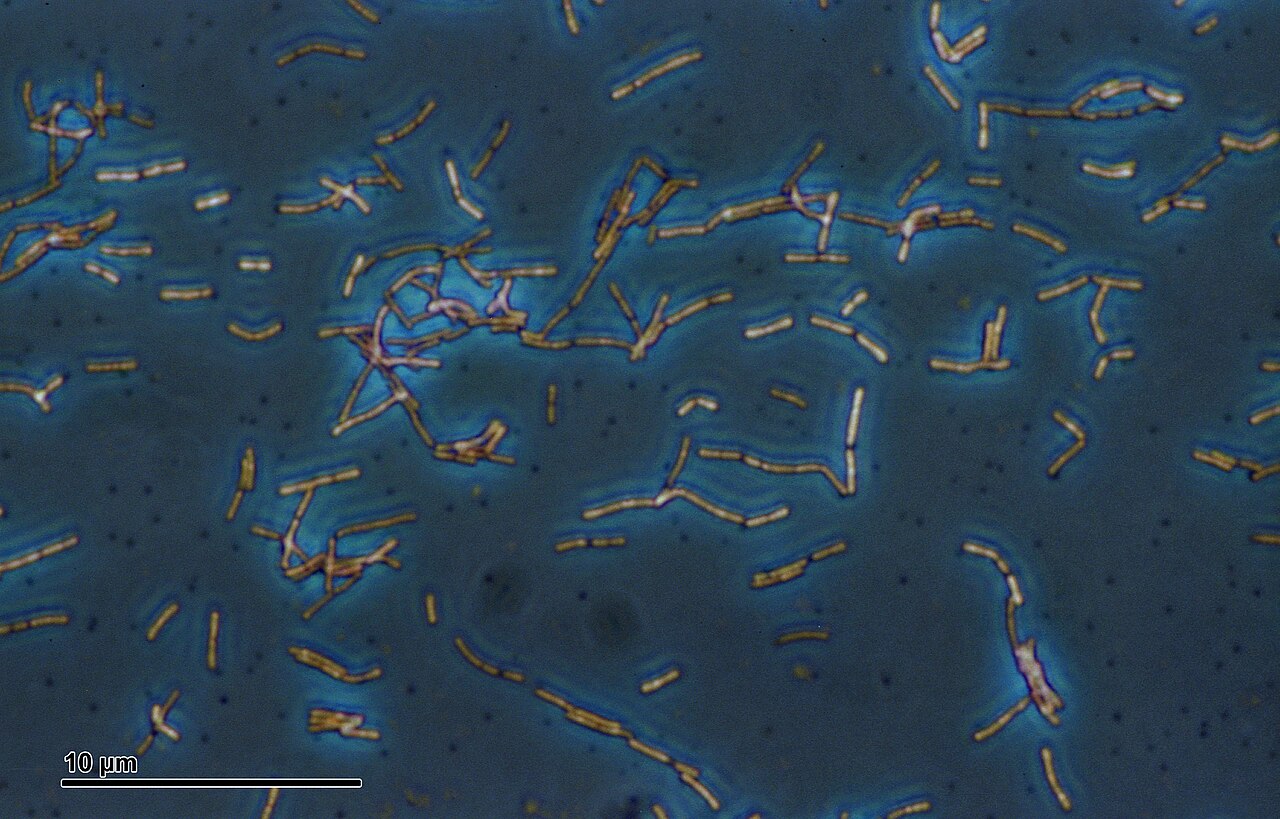
A probiotic is defined by a live microorganism identified to the strain level and delivered in an adequate amount for a studied benefit. Lactobacillus, Bifidobacterium, Saccharomyces, and Bacillus products are not interchangeable. Even two strains within the same species can differ in survival, antibiotic susceptibility, and clinical evidence.
Labels that list only a genus or a proprietary blend prevent readers from matching the product to a trial. Colony-forming units at manufacture may also differ from counts guaranteed through expiration. Storage temperature, moisture, and packaging influence whether the labeled organisms remain viable when used.
What recent evidence suggests
A 2025 meta-analysis of adult randomized trials reported that probiotics reduced antibiotic-associated diarrhea overall. A 2026 umbrella review covering 21 systematic reviews and 170 unique trials also found a preventive signal, while emphasizing overlap among reviews, variable risk of bias, and the need for strain-specific studies.
Pooled benefit does not mean every formulation works. Meta-analyses combine different antibiotics, ages, settings, organisms, doses, and definitions of diarrhea. The average result is most useful when a consumer can identify a product supported in a comparable population rather than choosing the largest CFU number.
One modern trial illustrates the specificity problem
The 2024 SPAADA trial tested a defined high-dose mixture containing several bacterial genera plus Saccharomyces boulardii in adults receiving antibiotics. Its findings apply to that formula, schedule, and setting. A gummy with one unspecified strain cannot claim equivalence.
Timing relative to antibiotics also depends on the organism. Bacterial probiotics may be separated from an antibiotic dose to reduce direct killing, while the yeast S. boulardii is not killed by antibacterial drugs. Exact instructions should follow the tested protocol and clinician advice rather than a universal social-media rule.
Diarrhea is not one diagnosis
Antibiotics can cause mild loose stools through several mechanisms, but significant diarrhea can reflect Clostridioides difficile infection or another illness. Fever, blood, severe abdominal pain, dehydration, frequent watery stools, or symptoms after hospitalization require medical attention. A probiotic should not delay testing or treatment.
Evidence for general antibiotic-associated diarrhea and for C. difficile-associated diarrhea are related but distinct. A review that reduces mild diarrhea does not automatically prove prevention of severe C. difficile disease, hospitalization, or recurrence. Claims should name the outcome actually measured.

Safety is usually good, not universal
Most healthy people tolerate probiotics, with gas or bloating among common complaints. Rare bloodstream infections with probiotic organisms have occurred, mainly in people who were severely ill, immunocompromised, in intensive care, receiving nutrition through catheters, or using broad-spectrum antimicrobials.
Preterm infants are a particularly sensitive group, and FDA has warned about invasive infections from probiotic use in hospitals. People with central venous catheters, major immune suppression, critical illness, or disrupted intestinal barriers should not self-start a live microbial product without specialist guidance.
How to choose without overclaiming
Look for full genus, species, and strain designations; CFUs guaranteed through expiration; storage instructions; and evidence in the relevant age group and antibiotic context. More strains and larger counts are not automatically better. Independent quality testing can verify identity and contamination, though it cannot prove efficacy.
Discuss the plan before the antibiotic course when possible, because timing of initiation may matter. The evidence supports a conditional conclusion: selected probiotics can lower antibiotic-associated diarrhea risk, but product-level matching and patient safety are essential. Buying a random high-CFU blend is not the same intervention studied in a randomized trial.
Antibiotic stewardship remains the more important prevention strategy: use antibiotics only when indicated, at the prescribed dose and duration, and report significant adverse effects. Probiotics do not protect against allergic reactions, resistant infections, or every disruption of the microbiome. They also should not be used to justify unnecessary antibiotics. The best research question is narrow—whether a defined live product reduces a defined diarrhea outcome during a particular antibiotic course—not whether probiotics broadly restore gut health.
Sources & further reading
This article is educational and does not diagnose, treat, or replace individual medical advice. Ask a qualified clinician or pharmacist about symptoms, medical conditions, and possible interactions before using supplements.