Magnesium Oxide for Constipation: Evidence, Dosing and Kidney Safety
Magnesium oxide improved constipation in short trials, but kidney function, medication timing and the elemental dose matter.
Magnesium oxide can work as an osmotic laxative, but use the lowest effective amount and get clinical advice when kidney function is reduced or symptoms persist.
Magnesium oxide works in the bowel, not as a wellness slogan
Magnesium oxide draws water into the intestine, which can soften stool and support bowel movements. That makes it a real laxative option, not simply another form in the supplement aisle. The same action can also cause diarrhea, cramping and electrolyte problems when the dose is too high or clearance is impaired.
This use is different from magnesium for sleep. A person choosing a glycinate capsule for bedtime is asking a different question from someone treating constipation with oxide. The salt, elemental amount, timing and desired effect all matter.
Two randomized trials found short-term benefit
A placebo-controlled trial in 34 women with chronic constipation found a response in 70.6% of the magnesium oxide group versus 25% with placebo after four weeks. Stool frequency, transit time and quality-of-life measures improved, although the small study cannot define long-term safety or the best dose for every patient.
A second randomized trial compared magnesium oxide, senna and placebo in 90 adults. Response rates were 68.3% with magnesium oxide, 69.2% with senna and 11.7% with placebo. The results support short-term efficacy, while also showing that another established laxative performed similarly.
The label can hide the amount that counts
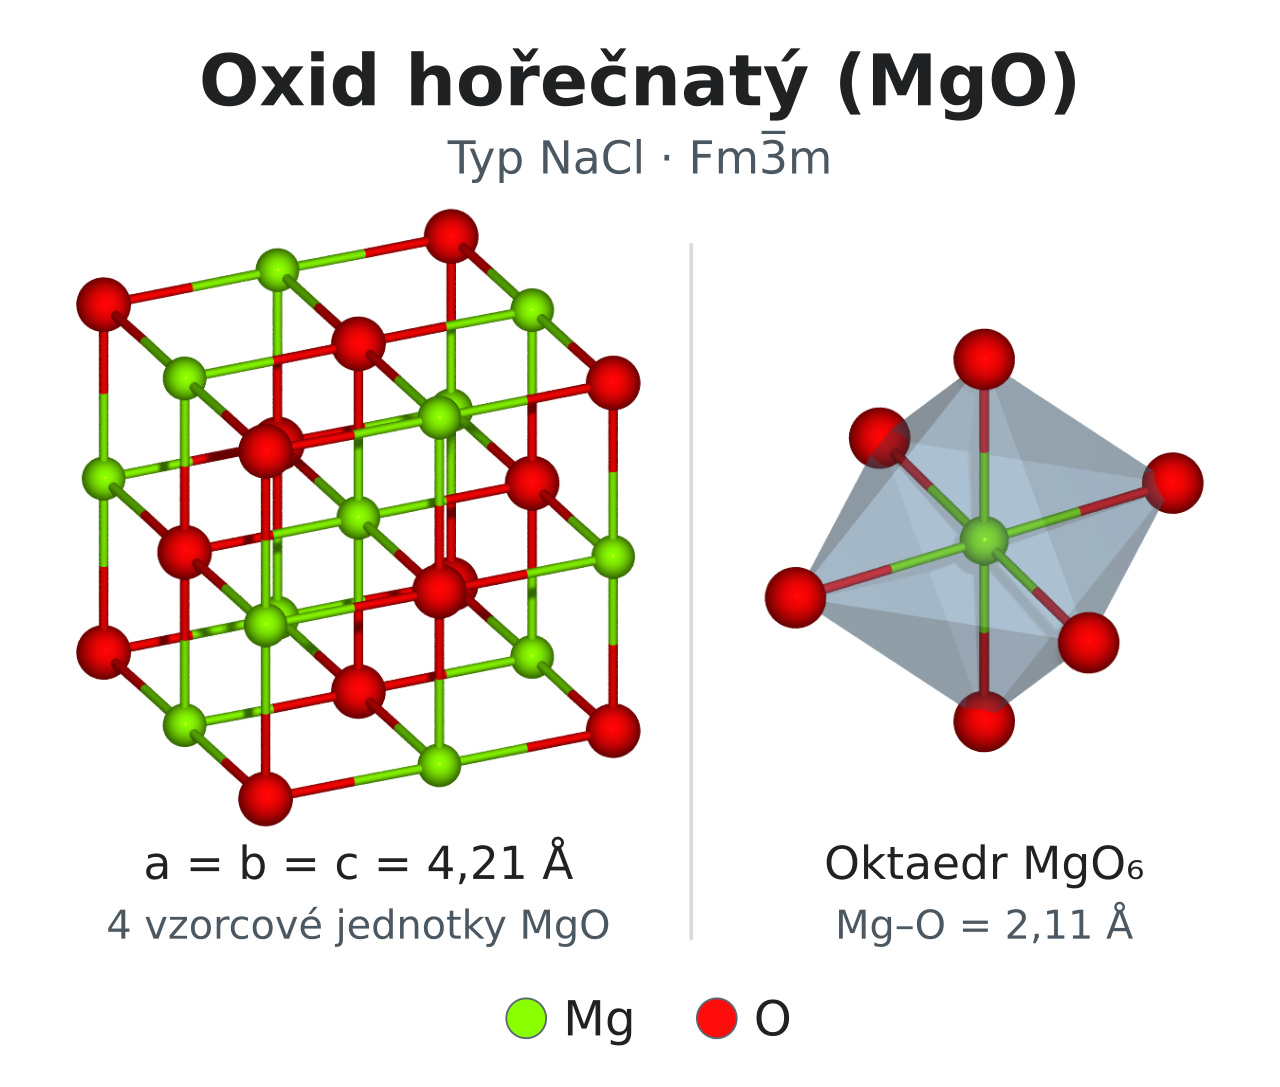
Compare the elemental magnesium amount, not only the weight of the oxide compound. Products differ in serving size, and several capsules may be required. Chelated minerals are often marketed for absorption or tolerance, but higher systemic absorption is not the goal when magnesium is being used mainly as an osmotic laxative.
Start only with the labeled or clinician-recommended amount. Rapidly escalating until diarrhea occurs is not a careful dosing strategy. A bowel diary can show stool frequency, consistency, pain and the need for rescue treatments without relying on memory.
Kidneys turn an ordinary dose into a different risk calculation
Healthy kidneys remove absorbed magnesium. Chronic kidney disease, acute kidney injury, older age with reduced filtration and very large or prolonged doses increase the risk of hypermagnesemia. Early symptoms can include nausea, weakness and low blood pressure; severe toxicity can affect breathing, heart rhythm and alertness.
Boron for testosterone and bones is another mineral claim that needs product-specific evidence rather than category assumptions. People with kidney disease should not self-treat repeatedly with magnesium laxatives. Medication interactions also matter because magnesium can reduce absorption of some antibiotics, thyroid medicine and bisphosphonates.
Know when constipation needs more than a bottle
Fiber supplements can help some patterns, but extra fiber is not right for obstruction, severe pain or every form of slow transit. Persistent constipation deserves a review of fluid intake, diet, activity, medicines, pelvic-floor function and medical causes. Blood in stool, vomiting, fever, unexplained weight loss or marked abdominal swelling needs prompt care.
For occasional use, choose a clear elemental dose, follow spacing instructions and stop if significant diarrhea or weakness develops. For chronic use, agree on a plan and follow-up with a clinician. A product can be effective in a trial and still be the wrong tool for a particular cause.
Compare options by the problem they solve
Polyethylene glycol, stimulant laxatives, fiber and prescription treatments work differently. Stool that is hard and infrequent may need a different plan from a feeling of blocked evacuation, opioid-related constipation or constipation with severe bloating. A short trial should have a defined goal, such as easier stools without urgency, rather than a race to daily diarrhea.
Review antacids and combination products because magnesium can appear in several places. Also count diarrhea from other medicines, which can turn a reasonable dose into excessive fluid loss. If magnesium oxide is used regularly, clinicians may consider kidney function and electrolytes based on age, dose and health history. Effective does not mean maintenance is automatically risk-free.
Pregnancy, childhood and frailty deserve product-specific advice rather than an adult over-the-counter routine copied from the shelf. Constipation lasting weeks, alternating with diarrhea or requiring repeated rescue doses should trigger reassessment. The goal is comfortable, predictable bowel function and an explanation for the pattern—not dependence on ever-larger amounts of an osmotic mineral.